The Unsettling Link Between Long COVID and Brain Damage: A Wake-Up Call for Medicine
Imagine your brain slowly deteriorating, not from age or injury, but from a virus most people shrug off in a week. That’s the grim reality emerging for Long COVID patients, where infections once deemed "mild" are now tied to profound, lasting neurological damage. As someone who’s followed this crisis closely, I’ve gone from skepticism to alarm—this isn’t just a post-pandemic footnote. It’s a harbinger of a looming public health catastrophe.
Dopamine: The Brain’s Currency for Motivation (And Why Losing It Matters)
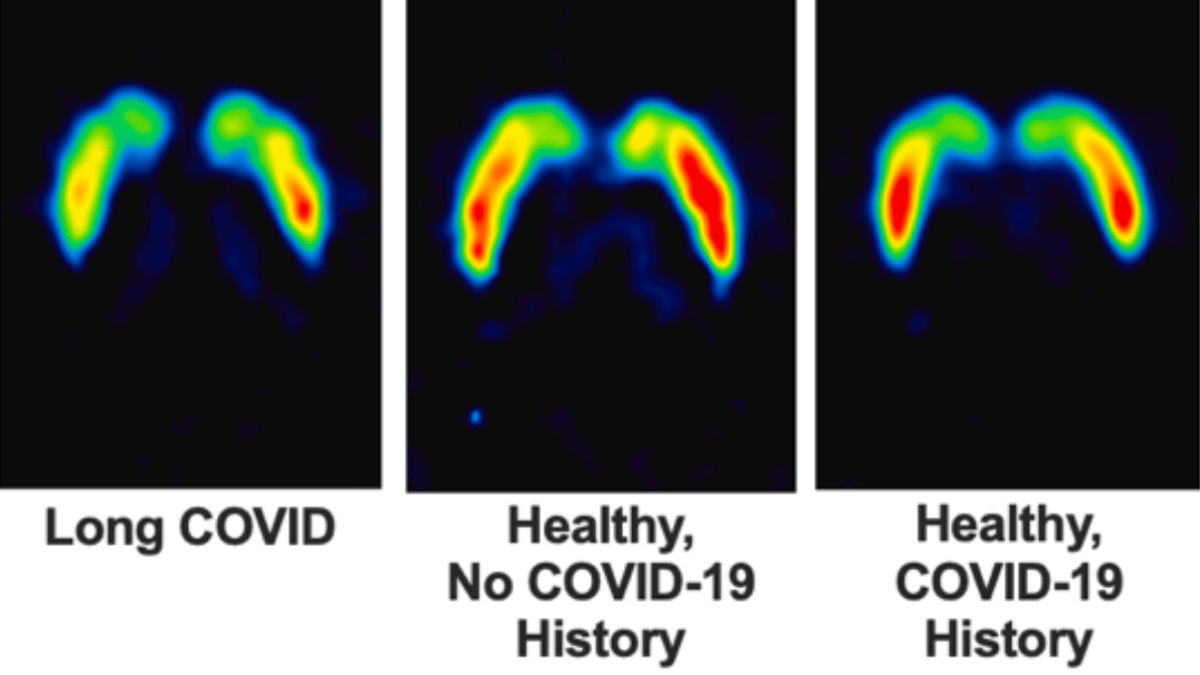
Let’s dissect the dopamine connection. This neurotransmitter isn’t just about feeling good; it’s your brain’s engine for action. When Canadian researchers found an 18% depletion of dopamine nerve endings in Long COVID patients, my first thought wasn’t about the number itself—it was about what this signifies: a literal erosion of people’s ability to engage with life.
Why this matters: Dopamine depletion isn’t abstract. From my perspective, this explains why otherwise healthy people suddenly struggle to get out of bed, process simple tasks, or find joy in hobbies. The striatum—the brain region affected—acts like a control panel for movement and motivation. Damage here doesn’t just cause fatigue; it rewires how people experience existence. What fascinates and horrifies me is how this mirrors early-stage Parkinson’s, yet gets dismissed as "mental health" issues in clinics worldwide.
The Scans Don’t Lie—So Why Are We Ignoring Them?
Here’s what keeps me up at night: For years, Long COVID sufferers were told their symptoms were psychological. Now we have visible brain changes on PET scans, and suddenly the medical establishment leans in? This isn’t just hypocrisy—it’s a symptom of a deeper problem. We’ve built healthcare systems that prioritize visible, quantifiable damage over patient experiences. As I see it, this study’s greatest contribution might be forcing doctors to confront what they can no longer see with their own eyes.
A key distinction: Unlike Parkinson’s, where motor symptoms dominate, Long COVID’s dopamine loss manifests as cognitive fog and emotional flatlining. This raises a terrifying question: Are we witnessing the birth of a new neurodegenerative syndrome? Or have we simply failed to recognize similar conditions like ME/CFS for what they’ve always been—biological illnesses with psychiatric consequences, not the other way around?
The Treatment Mirage: Why Hope Is Still Premature
Jeffrey Meyer’s upcoming clinical trial using dopamine-targeting drugs sounds promising—until you consider the context. Repurposing medications isn’t innovation; it’s desperation. What many overlook is that this approach treats symptoms, not underlying pathology. From my analysis, we’re essentially trying to patch a sinking ship with band-aids. Even if the trial “succeeds,” we’re ignoring larger questions:
- Why does a virus cause autoimmune attacks on dopamine pathways?
- How do we repair neuronal infrastructure, not just stimulate remaining cells?
- What happens to patients whose damage progresses beyond dopamine systems?
Meanwhile, the 10-20% of children with Long COVID aren’t just statistics—they’re a generation at risk for developmental disruptions we don’t yet understand. When I consider the ethical implications, it’s hard not to feel we’re failing both current and future patients.
Beyond the Headlines: A Larger Pandemic of Ignorance
Let’s zoom out. This study matters not just for Long COVID, but for how we understand post-viral illnesses entirely. For decades, chronic fatigue syndrome patients were gaslit into therapy couches. Now we’re seeing identical symptom clusters validated biologically. If you take a step back, this isn’t just about SARS-CoV-2—it’s about dismantling a medical paradigm that separates mind and body.
The hidden implication: We might be looking at a new category of neuroimmune disorders triggered by infections. The 65 million+ Long COVID cases are the tip of an iceberg that could include post-Lyme, post-mononucleosis, and other mysterious syndromes. What makes this particularly fascinating is how it challenges our siloed approach to medicine—neurology, immunology, and psychiatry can no longer afford to work in isolation.
The Uncomfortable Truth We’re Not Facing
I’ll leave you with this: Even if dopamine treatments work, we’re still missing the bigger picture. The real story here is about vulnerability. We’ve created a world where a microscopic particle can unravel lifetimes of health because we underestimated biology’s complexity. This research should be our Sputnik moment—a catalyst for revolutionizing how we treat chronic illness.
But will we invest in bold solutions, or continue playing catch-up while patients suffer? The answer will define medicine’s legacy in this pandemic era. Personally, I’m not optimistic—but I remain hopeful that visible brain scans might finally force the change we’ve needed for decades.